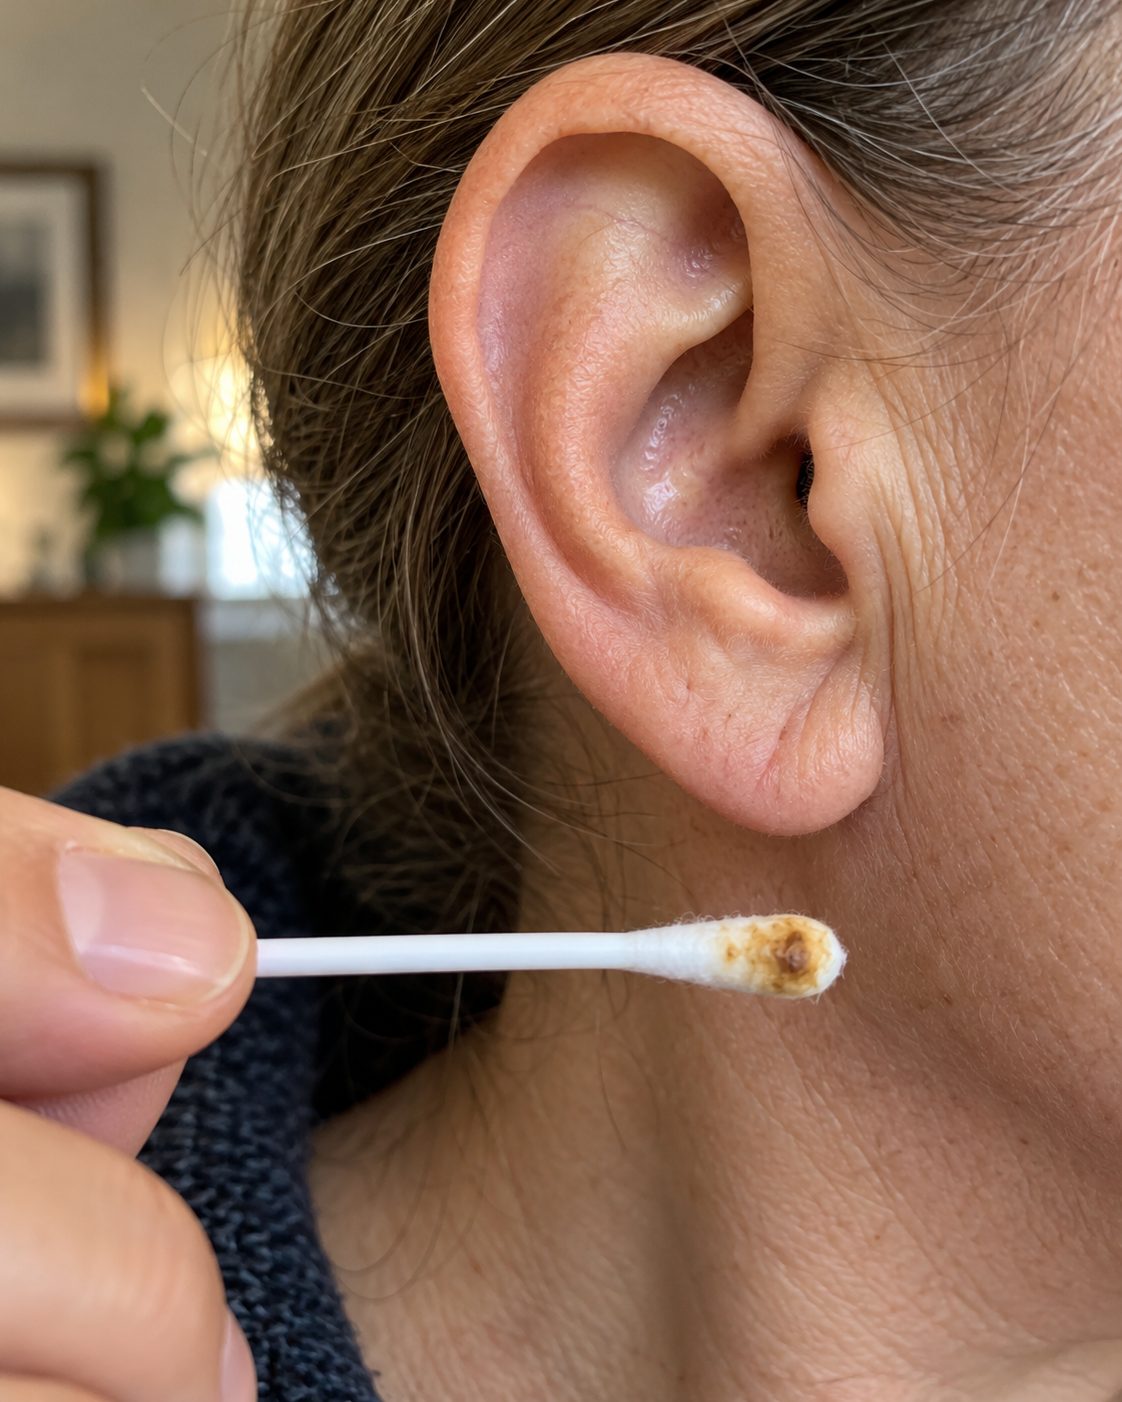
You clean your ear with a cotton swab, see wax on the tip, and expect everything to sound clearer. Instead, your ear still feels plugged—or feels more blocked than before.
That can happen because a swab removes some visible wax while pushing other wax farther into the ear canal. Less commonly, part of the cotton tip can come off and remain inside. A swab can also irritate or injure the ear. The wax you see does not tell you what remains beyond your view.
The safest next step is to stop putting anything into the canal. Persistent blockage deserves an examination, particularly if it started or worsened after swabbing.
If your hearing drops suddenly, seek medical care immediately. Do not assume it is wax or wait several days for ear drops to work. A sudden inner-ear hearing problem can also feel like a plugged ear.
Why wax can come out while a blockage stays behind
A cotton swab is not a vacuum. It may collect wax along its surface while the tip presses other wax inward.
This explains the frustrating combination of a dirty swab and an ear that still feels stopped up. Seeing wax on the cotton confirms that you touched wax; it does not confirm that you cleared the canal.
Ear specialists warn that attempts to clean with swabs can push wax deeper and worsen an existing blockage.
Imagine wiping the entrance to a narrow space while pressing material farther into it. The cloth may look dirty afterward even though the space is more obstructed.
That is only an illustration, not a way to diagnose your own ear. You cannot tell how much wax remains, how close it is to the eardrum, or whether something else is responsible by inspecting the used swab.
Repeated attempts add uncertainty. A second or third swab does not provide a reliable measure of progress.
Earwax is supposed to be there
Earwax, also called cerumen, is a normal protective material. It helps lubricate the ear canal and trap debris.
In most ears, wax and shed skin gradually move outward. Ordinary jaw movements help that process. Wax near the opening can dry, flake, and leave without you digging it out. Removing every trace is unnecessary.
A little wax on a washcloth is not evidence that your ears are dirty. Nor does an ear need to feel freshly scrubbed inside to be clean.
The problem is wax that causes symptoms or prevents a clinician from examining the ear when needed. That is different from simply having wax.
If your ears feel comfortable and your hearing has not changed, there is usually no reason to investigate the canal with a swab. Routine outer-ear washing is enough for most people.
Could the cotton itself be stuck?
Yes. Cotton or a cotton-swab tip can become a foreign object in the ear canal. This is a recognized problem in adults, not just something that happens when children put objects in their ears.
Suspect this if the swab comes out with its tip missing or noticeably incomplete, particularly if the ear immediately feels different.
Keep the swab if it helps you show a clinician what may be missing. Tell the office or urgent-care staff that you think cotton is lodged in the ear, rather than describing the problem only as “earwax.”
Do not insert another swab to check. Do not ask someone to reach in with tweezers, even if they have a flashlight. Probing can move an object deeper or damage the canal. Avoid putting liquid into an ear with a suspected foreign object or injury while arranging care.
Contact a healthcare professional promptly for assessment and removal. If there is pain, bleeding, dizziness, or a hearing change, seek urgent evaluation.
Cotton is not wax, so a wax-softening product is not a substitute for checking and removing a retained tip.
A blocked feeling does not prove there is a blockage
An ear can feel full for more than one reason.
Wax is one possibility. Others include irritation or infection of the ear canal, fluid behind the eardrum, and certain hearing problems. These can feel similar from the outside.
The timing matters, but it does not settle the diagnosis. If you used a swab because your ear already felt plugged, the original problem may still be present. If discomfort began during swabbing, the canal or eardrum may have been injured.
A useful account for your appointment might be:
“I noticed muffled hearing yesterday. I used a swab this morning, and the fullness became worse. I did not see blood, and the cotton tip appears intact.”
That kind of sequence gives the clinician more useful information than a guess about what must be inside.
You do not need to identify the cause before asking for help.
What to do right after swabbing
If the ear remains blocked, pause before trying another remedy.
- Stop inserting objects. Put away the swabs, scoops, and other tools.
- Check the used swab. Look at the tip outside your ear. Note whether any cotton appears missing.
- Notice the symptoms. Pay attention to hearing changes, pain, ringing, dizziness, bleeding, or drainage.
- Choose care based on those symptoms. Sudden hearing loss needs immediate care. Suspected retained cotton or an injury needs prompt assessment.
- Arrange an examination if the blockage persists. Avoid treating an uncertain problem repeatedly as wax.
Do not keep testing the ear by pushing on it or trying to reach “just a little farther.” The aim is to give the next person examining it a clear account, without adding another injury.
If you are unsure whether the hearing change is sudden or significant, describe it to a healthcare professional promptly rather than using a home experiment to decide.
When can wax-softening drops be reasonable?
For a known, uncomplicated wax problem, a clinician or pharmacist may recommend an over-the-counter product.
But drops are not the right starting point for every ear that feels blocked—especially after a swab has caused pain or may have left cotton behind.
Some products contain carbamide peroxide to soften and loosen excessive wax. Their labels include important restrictions: do not use them with ear pain, drainage, irritation, dizziness, or a known or suspected eardrum injury without medical advice. Previous ear surgery also changes what is safe.
Before choosing drops, explain:
- Whether the fullness began before or after swabbing.
- Whether the cotton tip is intact.
- Whether you have pain, drainage, bleeding, or dizziness.
- Whether you have ear tubes, a hole in the eardrum, or previous ear surgery.
- Whether a clinician has previously confirmed recurrent wax blockage.
If a professional recommends a product, follow that product’s directions. Do not substitute a stronger household chemical or combine several ear-cleaning liquids.
For common carbamide-peroxide products, labeling limits self-treatment to no more than four days and advises medical review if excessive wax remains. Continuing indefinitely is not the plan.
Why a home flush may be the wrong next step
A blocked sensation after swabbing is not a good reason to automatically reach for a syringe.
Before irrigation, it matters whether the eardrum is intact, whether there is an infection or injury, and whether the material is wax or a foreign object.
People with ear tubes, an eardrum perforation, previous ear surgery, diabetes, weakened immunity, or certain ear-canal skin conditions need individualized advice. Ear specialists specifically caution against irrigation in several of these situations.
Do not use a shower jet, water flosser, or improvised pressurized device in the ear. If irrigation is appropriate, your clinician can explain the suitable method or perform it.
There is no need to prove you can manage it at home. Having someone look first is a practical way to avoid treating the wrong problem.
Signs that should move care higher on your list
Seek immediate medical assessment for a sudden hearing drop, whether it happens all at once or develops over a few days. It may affect one ear and come with ringing, dizziness, or fullness. Treatment for sudden inner-ear hearing loss is time-sensitive.
Seek urgent care after swabbing if you have:
- Significant or worsening ear pain.
- Bleeding or fluid coming from the ear.
- New dizziness or a spinning sensation.
- A new hearing change.
- A suspected retained cotton tip, especially with symptoms.
Ear injuries and foreign objects may require special instruments and a careful examination. Do not continue probing while waiting to be seen.
Fever, persistent earache, foul-smelling drainage, or worsening symptoms also warrant prompt medical attention.
If the main issue is gradual fullness without these warning signs, arrange a regular appointment when it persists or recurs. You do not have to wait until the ear becomes painful.
What happens at an ear examination?
A clinician looks into the canal using a lighted instrument called an otoscope. This can help show whether wax, cotton, or another visible problem is present.
When wax needs removal, options may include a small instrument, suction, or irrigation, depending on the ear and your medical history. Softening drops may also be recommended.
A retained cotton tip requires an approach suited to its position and shape. Some objects can be removed in an outpatient setting; others need an ear, nose, and throat specialist. Adequate lighting and direct visualization matter.
Tell the clinician about previous removal attempts and anything you put into the ear. This is useful information, not something to feel embarrassed about.
Ask what was found and what you should do afterward. If the ear still feels blocked or hearing remains reduced after removal, say so before leaving. Clearing visible material does not automatically explain every hearing symptom.
What if you wear hearing aids?
A change in hearing can make it tempting to clean both the hearing aid and the ear more aggressively.
Follow the manufacturer’s cleaning instructions for the device. Earwax and drainage can affect hearing aids, but a tool designed to clean a hearing-aid part should not be inserted into your ear canal.
If a soft dome or other part appears to be missing, mention that when arranging an examination. Hearing-aid components are another recognized type of ear-canal foreign object.
For recurring wax problems, ask your hearing-care professional or clinician whether periodic ear checks would help. The schedule should reflect your own history.
Bring the hearing aid or the missing-part information to the visit if relevant. It can help distinguish a device problem from a problem inside the ear.
A simpler routine for everyday ear care
You can keep your ears clean without cleaning inside them.
- Use a soft, damp cloth on the visible outer ear.
- Wipe away wax that has already reached the outside.
- Keep the cloth, fingers, and swabs out of the canal.
- Ask about recurring symptoms instead of adding more cleaning.
The canal generally handles its own routine cleaning. Persistent itching or fullness is a reason to seek advice, not a signal that you need to scrub deeper.
Avoid ear candles. They do not remove earwax and can cause burns or damage. Replacing a cotton swab with a different scraping tool does not make inside-the-ear cleaning safe.
If swabbing has become part of your daily routine, put the swabs somewhere other than beside your toothbrush or shower supplies. A small change in the setup can help you stop reaching for them automatically.
The wax on the tip is only part of the story
A swab can collect wax while leaving a deeper blockage behind. It can also leave cotton or cause an injury, so continued fullness deserves more than another cleaning attempt.
Stop putting objects into the canal, get suspected retained cotton checked promptly, and treat sudden hearing loss as urgent.
For everyday care, clean the outside. For a persistently blocked ear, let someone look inside.
For another small symptom that can leave you wondering what’s going on, read why your eyelid keeps twitching – and when it’s worth getting checked. For a change of pace, try this chef’s trick for cooking rice or compare higher-protein, lower-calorie McDonald’s orders.


